
Where Behavioral Health Operations Break Down Between Levels of Care

Where Behavioral Health Operations Break Down Between Levels of Care
Changing a patient’s level of service is a clinical decision, but it sets off a chain of verification, authorization, scheduling and billing work. Here is where that chain tends to break, and what it costs.
The Transition Is More Than a Clinical Decision
A patient finishes inpatient treatment and is clinically ready to step down to a partial hospitalization program (PHP). The clinical decision has been made, but the transition is not done. The team still has to answer five questions:
- Is the next level of service covered?
- Is a new authorization required?
- Has the necessary clinical documentation been submitted?
- Has the payor responded?
- Can the patient be scheduled for this step-down care?
If even one goes unanswered, the impact goes beyond administrative inconvenience. Staff repeat work or resubmit authorizations, the patient’s transition is delayed, and the provider faces slower reimbursement or a denied claim.
That is what turns a change in level of care into an operational and financial challenge.

A change in level of care is a clinical decision. Executing it successfully takes connected administrative workflows. |
What Changes When the Level of Service Changes?
A clinical recommendation is only the first step. When a patient moves between levels of care, the organization has to re-verify and realign several processes at once:
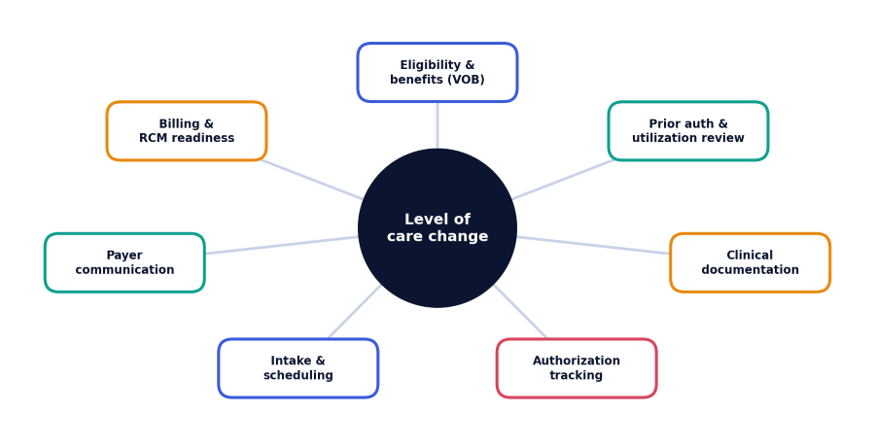
- Eligibility and benefits verification (VOB): re-confirm coverage limits for the new service line.
- Prior authorization and utilization review (UR): establish medical necessity for a different level of acuity.
- Clinical documentation: compile progress notes and treatment plans to the receiving program’s requirements.
- Authorization tracking: monitor active status to prevent coverage gaps.
- Intake and scheduling: align clinical handoffs with real-time capacity and approved start dates.
- Payor communication: manage peer-to-peer reviews, information requests and follow-ups.
- Billing and RCM readiness: make sure claim codes match the approved authorization.
Requirements vary by payor and facility, but the challenge is constant: several teams need the right information at the same moment.
Where the Handoff Breaks
Transitions rarely fail because teams aren’t working hard. They fail because disconnected systems create predictable handoff failures:
- Information doesn’t move with the patient. Receiving teams re-request clinical or insurance details already gathered at intake.
- Authorization requirements are unclear. Staff lose hours working out whether a service change needs a new authorization, an extension or a full clinical packet.
- Submissions are incomplete. Missing treatment plan updates or clinical notes trigger rejections and requests for more information.
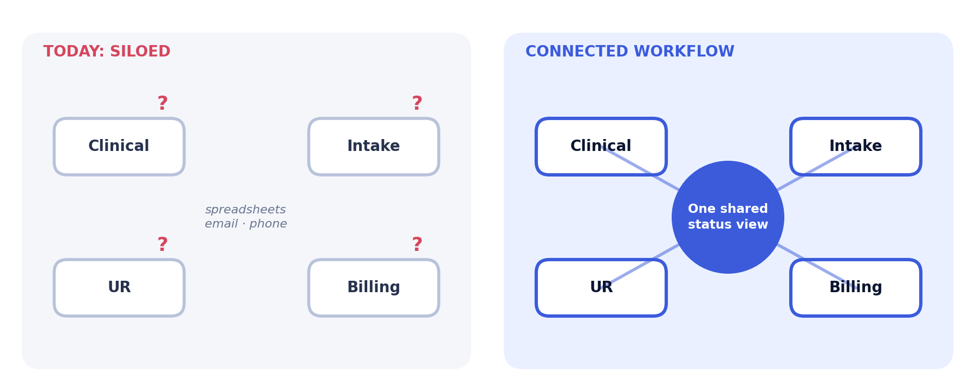
- Status is siloed. Clinical, intake, UR and billing each use different software or manual logs, so nobody has a single source of truth for transition readiness.
- Deadlines are managed by hand. Authorizations nearing expiration live on local spreadsheets, and routine renewals become fire drills.
Two Common Transitions
Direction matters. Step-downs are planned and run against a discharge date. Step-ups are urgent and run against patient risk. The same administrative gaps hurt in different ways.
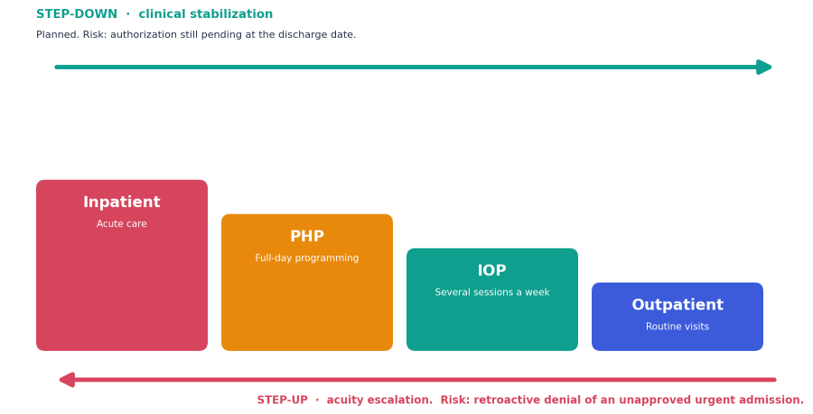
Step-down: inpatient to PHP or IOP
A patient moves from an acute setting to a structured outpatient program as clinical stability improves.
- Clinical and intake: the inpatient team recommends step-down, and intake confirms PHP/IOP program availability.
- Insurance verification: staff review the VOB to see whether the current authorization covers the step-down or a new prior authorization is needed.
- Utilization review: documentation goes to the payor to justify medical necessity for the lower level of care.
- Scheduling: intake and program scheduling are finalized once authorization is secured.
Where it breaks • Missing clinical documentation: submissions lack details specific to the new level of care and need corrections. • Payor delays: the authorization is still pending as the planned transition date approaches. • Communication gaps: intake and scheduling can’t see real-time authorization status, which holds up placement. |
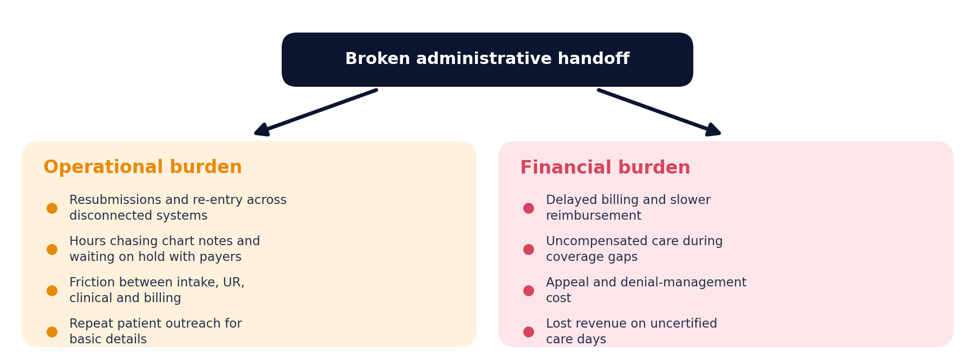
OPERATIONAL Resubmissions, repeated payor follow-ups, delayed scheduling and staff friction. | FINANCIAL Delayed authorization leads to delayed billing, unbilled service days or claim denials. |
Step-up: outpatient or IOP to PHP or inpatient
A patient moves to a more intensive level of care because of clinical decompensation or increased risk.
- Clinical evaluation: outpatient or IOP staff identify increased acuity and formally recommend a step-up.
- Urgent VOB and coverage: staff confirm higher-level acute benefits are active and check in-network facility requirements.
- Urgent prior authorization: UR rapidly submits notes showing medical necessity, within the payor’s urgency requirements.
- Admission and placement: intake coordinates bed availability, transport and handoff once approval or an emergency protocol is triggered.
Where it breaks • Authorization bottlenecks: standard review timelines don’t match clinical urgency, and peer-to-peer reviews happen while the patient waits. • Strict acuity criteria: the payor disputes medical necessity for an inpatient stay versus PHP and asks for more evidence. • Record handoff: outpatient records are delayed or don’t reach the inpatient medical team at intake. |
OPERATIONAL High administrative load under time pressure, duplicate data entry, urgent follow-ups and risk to patient safety during delays. | FINANCIAL Uncertified admissions risk retroactive denial, which means costly appeals and uncompensated care. |
Step-up vs. step-down at a glance
Dimension | Step-down (inpatient to PHP/IOP) | Step-up (outpatient/IOP to PHP/inpatient) |
Primary driver | Clinical stabilization | Acuity escalation or safety risk |
Urgency | Working to a scheduled discharge date | Expediting immediate placement |
Main administrative risk | Authorization delays extend the stay or push back enrollment | Retroactive denial of an unapproved urgent admission |
Documentation needed | Step-down medical necessity and outpatient treatment plan | Crisis documentation and acute medical-necessity justification |
Reauthorization: The Transition That Happens During Care
Not every transition involves a new program. Reauthorization is a transition in coverage duration while the patient stays in their current program. As the authorized units near their limit, the UR team has to:
- Track the upcoming expiration date.
- Compile updated clinical progress notes.
- Submit the reauthorization request before the payor’s cutoff.
- Monitor the payor decision to avoid an interruption in care.
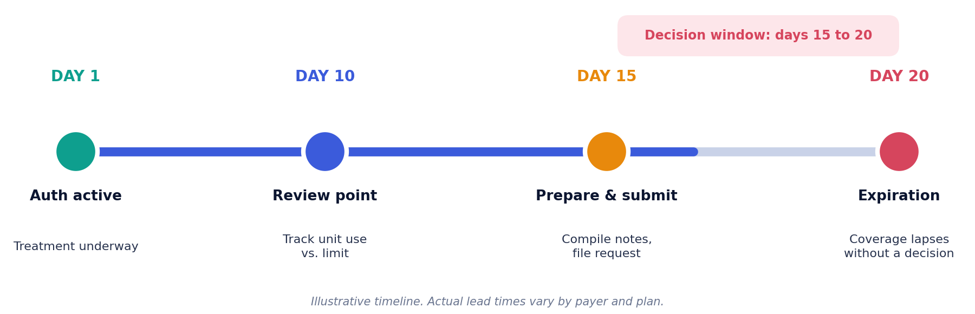
Where it breaks: when expiration dates live on static spreadsheets, deadlines get missed. That leads to emergency submissions, rushed documentation, delayed payor decisions and gaps in approved treatment days.
Twin Costs of a Broken Transition
When administrative handoffs fail, the cost lands in two places:
What a Connected Workflow Looks Like
The fix isn’t working faster. It is moving from disconnected tools to connected workflow management. A connected behavioral health workflow handles transitions by:
- Detecting service changes: recognizing automatically when a patient’s level of care changes.
- Triggering smart checklists: generating role-specific tasks for intake, UR and billing.
- Surfacing VOB rules: showing payor-specific authorization rules for the target level of care.
- Centralizing status tracking: giving clinical, intake and revenue teams one view of authorization milestones.
- Automating expiration alerts: flagging reauthorizations days before they lapse.
- Handing off cleanly to RCM: passing verified authorization details to billing for clean claims.
This is where CloudAstra comes in: orchestrating workflows across intake, VOB, prior authorization, utilization review, patient flow and revenue cycle, so teams can focus on moving care forward. |
What Behavioral Health Leaders Should Look For
To gauge your operational readiness, ask these questions:
- Identification: who flags that a patient is ready for a level-of-care transition?
- Verification: how quickly are benefits re-verified for the target service line?
- Requirements: how do staff learn the exact prior authorization rules for each payor?
- Tracking: can intake, UR and billing see authorization status in real time?
- Documentation: who checks that progress notes meet payor medical-necessity criteria?
- Handoffs: how does intake know the moment an authorization clears for scheduling?
- Revenue alignment: how does billing confirm authorization codes match services rendered before claims go out?
If answering these means digging through spreadsheets,
email chains and manual system checks, your organization has a clear
opportunity for workflow transformation. |
Conclusion
A change in level of care begins with a clinical decision, but carrying it out is an operational discipline.
When intake, UR, scheduling and billing operate in silos, one small mistake creates rework at every later step. Improving these transitions is not only about streamlining paperwork. It is about getting patients into the care they need smoothly while protecting your organization’s financial health.
CloudAstra connects intake, VOB, prior authorization, UR and revenue cycle management, giving teams the connected workflows they need to cut friction, prevent denials and keep patient care moving.
SEE CARECHORD ON YOUR OWN WORKFLOWWalk through verification, utilization review or claims, whichever is costing your team the most time today. |
www.cloudastra.ai · info@cloudastra.ai · +1 (408) 596-9289
“We help bring care back into healthcare.”